
Original Source: Journal of Clinical Psychiatry, all rights reserved. —
Late-onset mania, occurring after the age of 50 years, frequently signals an organic etiology rather than primary bipolar disorder1. The concept of vascular mania, characterized by later onset, neuroimaging evidence of cerebrovascular injury, and cognitive impairment, provides a useful, though not always confirmable, framework for such presentations.2 We report a case in which acute pontine infarction, autoimmune hyperthyroidism, and atrial fibrillation (AF) converged to produce late-onset mania with psychotic features in a medically complex 61-year-old man and highlight multidisciplinary management and electroconvulsive therapy (ECT) as the cornerstone of sustained remission.
Case Report
Mr A, a 61-year-old man with a history of hypertension, type 2 diabetes mellitus, chronic obstructive pulmonary disease, and active tobacco use, presented with a 1.5-month history of anger outbursts, overtalkativeness, tall claims, irritability, and decreased need for sleep. He had experienced 1 prior similar episode. On mental state examination, he demonstrated psychomotor agitation, pressured and tangential speech, an irritable and expansive mood with flight of ideas, and delusions of grandiosity and persecution. Of note, he harbored a persistent monothematic preoccupation with a land deal in which he believed he had lost a large sum of money, a theme to which he returned perseveratively across interviews despite redirection and that receded only insidiously as the manic episode resolved with treatment. Attention was severely distractible; insight was grade II. The Young Mania Rating Scale (YMRS)3 score was 24 (moderate-to-severe), and the Mini-Mental State Examination (MMSE)4 score was 24/30.
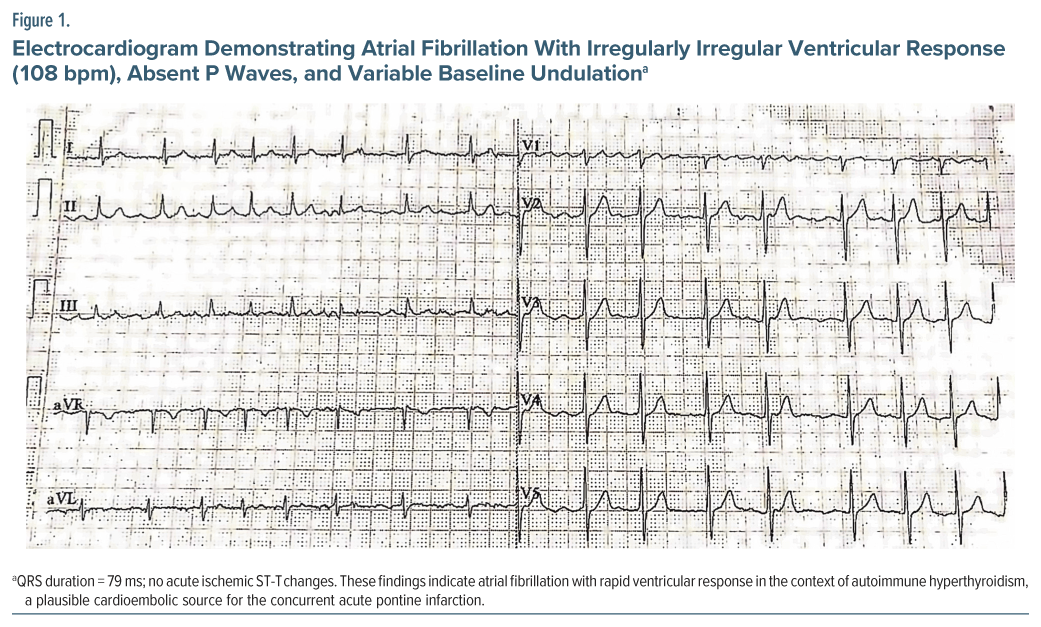
Investigations revealed suppressed thyroid-stimulating hormone (0.010 mIU/L; reference range, 0.40–4.05 mIU/L) with elevated free triiodothyronine (13.70 pmol/L; reference range, 4.26–8.10 pmol/L) and free thyroxine (41.0 pmol/L; reference range, 10.0–28.2 pmol/L) and positive antithyroid peroxidase antibodies, confirming autoimmune hyperthyroidism.5 Magnetic resonance imaging (MRI) of the brain (3 T) demonstrated 2 temporally distinct pathological layers: (1) acute diffusion-restricting foci in the right anterior pons, consistent with recent infarction, and (2) established encephalomalacia and gliosis in the left parieto-temporo-occipital subcortical white matter, a chronic lacunar infarct in the right corona radiata, and diffuse cerebro-cerebellar atrophy. Mild hyponatremia (Na 130 mmol/L) and poorly controlled glycemia (fasting blood sugar 229 mg/dL) were also documented. Electrocardiogram confirmed AF at 108 bpm (Figure 1). The acute pontine infarction, occurring in the setting of AF, is consistent with a cardioembolic mechanism.6 A diagnosis of bipolar affective disorder (International Classification of Diseases, Tenth Revision: F31.2), current manic episode with psychotic symptoms, with organic contributions consistent with the vascular mania framework, was established.2
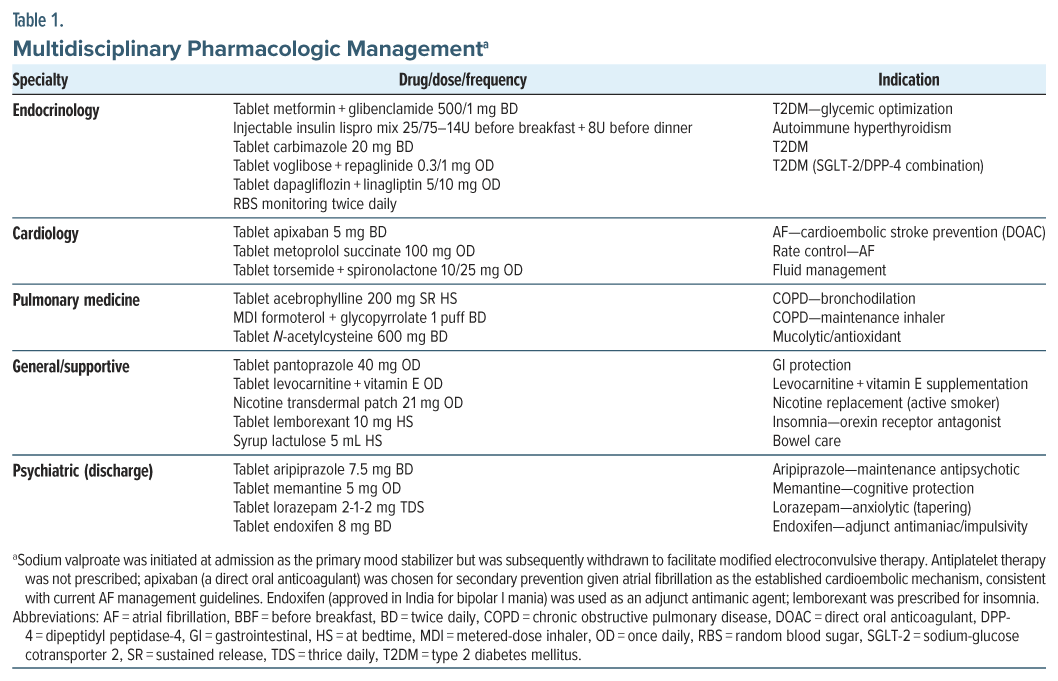
Sodium valproate was started as the primary mood stabilizer alongside aripiprazole and lorazepam; however, valproate was subsequently withdrawn to facilitate a course of modified ECT (MECT), given the severity and the medical complexity precluding aggressive pharmacologic escalation. Nine MECT sessions were administered (charge 480 mC, frequency 62.5 Hz, generalized tonic-clonic seizure, mean motor siezure duration 25 seconds), achieving a final YMRS score of 8—a reduction of 16 points from baseline. Memantine 5 mg once daily was added for cognitive protection given the MMSE score and vascular burden. Multidisciplinary management included apixaban (direct oral anticoagulation [DOAC] for AF-related cardioembolic stroke prevention), carbimazole for hyperthyroidism, and specialist endocrinology, cardiology, and pulmonary medicine input (Table 1 provides the full drug list).
Discussion
This case illustrates vascular mania driven by 3 converging organic mechanisms. The MRI finding of acute pontine diffusion restriction, against a background of chronic white matter disease, reframes the etiology from static vascular vulnerability to an active precipitant, temporally linked to the current episode via cardioembolic AF.2,6 The patient’s perseverative preoccupation with financial loss, resolving in parallel with YMRS improvement, is itself a soft frontal-subcortical sign consistent with the pontine and periventricular pathology. Thyrotoxicosis exerts direct neuropsychiatric effects through adrenergic and monoaminergic dysregulation.5 Valproate withdrawal to enable ECT, with YMRS score reduction from 24 to 8 over 9 sessions, underscores ECT primacy when pharmacotherapy is medically constrained. Apixaban rather than antiplatelet therapy reflects guideline-concordant secondary prevention for AF-related cardioembolic stroke.6
Conclusion
Clinicians encountering late-onset mania in the presence of AF should obtain MRI with diffusion sequences to identify acute infarcts rather than assuming chronic vascular burden alone. The dual therapeutic implications are as follows: ECT as the primary psychiatric intervention when pharmacotherapy is constrained by medical complexity, and DOAC over antiplatelet therapy for cardioembolic secondary prevention.
Article Information
Published Online: October 27, 2026. https://doi.org/10.4088/PCC.26cr04259
© 2026 Physicians Postgraduate Press, Inc.
Prim Care Companion CNS Disord 2026;28(5):26cr04259
Submitted: April 24, 2026; accepted July 16, 2026.
To Cite: Pant V; Sood K; Bhatia A, et al. Vascular mania in late life: acute pontine infarction, autoimmune hyperthyroidism, and atrial fibrillation converging in a 61-year-old man. Prim Care Companion CNS Disord 2026;28(5):26cr04259.
Author Affiliations: Department of Psychiatry, Shri Guru Ram Rai Institute of Medical and Health Sciences & Shri Guru Ram Rai University, Patel Nagar, Dehradun, Uttarakhand, India (all authors).
Corresponding Author: Shobit Garg, MD, DPM, Department of Psychiatry, Shri Guru Ram Rai Institute of Medical and Health Sciences, Patel Nagar, Dehradun – 248001, Uttarakhand, India ([email protected]).
Financial Disclosure: None.
Funding/Support: None.
Patient Consent: Consent was received from the patient to publish the case report and figure, and information has been de-identified to protect patient anonymity.
ORCID: Shobit Garg: https://orcid.org/0000-0001-5913-9021
Journal of Clinical Psychiatry, all rights reserved.