
Original Source: Journal of Clinical Psychiatry, all rights reserved. —
posttraumatic stress disorder (PTSD) is highly prevalent among military and public safety personnel and is frequently accompanied by comorbid conditions such as depression, anxiety, chronic pain, and substance use disorders.1 Across countries, clinical practice guidelines play a critical role in standardizing PTSD treatment by translating evidence into actionable recommendations for clinicians. Several international bodies produce PTSD guidelines, including the National Institute for Health and Care Excellence,2 the Australian National Health and Medical Research Council,3 and the US Department of Veterans Affairs/Department of Defense (VA/DoD).4 While guidelines differ in scope and some specific recommendations, they share common priorities: emphasizing trauma-focused psychological therapies as first-line interventions, recommending selective serotonin reuptake inhibitors (SSRIs) and serotonin-norepinephrine reuptake inhibitors (SNRIs) as first-line pharmacotherapies, and discouraging routine use of agents such as benzodiazepines due to safety risks and limited evidence.2,3
Emerging evidence highlights divergence between both research findings and documented practice with guideline recommendations. A meta-analysis found that while psychotherapies were generally effective, pharmacotherapies were comparably effective, and the combination of psychotherapy and pharmacotherapy consistently yielded a larger effect size relative to either monotherapy alone.5 Further, a program evaluation of prescribing practices within a single clinic found substantial variability in the types and combinations of medications used, reflecting both patient complexity and clinician preference.6 However, beyond this single-site analysis, prescribing patterns remain unexamined, particularly within Canada’s network of operational stress injury (OSI) clinics, which provide specialized care for military members, veterans, and Royal Canadian Mounted Police (RCMP) personnel with complex trauma-related presentations.
In Canada, OSI clinics serve as the dedicated national network for assessing and treating military- and service-related PTSD. Among Canadian military populations, PTSD is commonly associated with service training, combat exposure, deployment-related trauma, peacekeeping and humanitarian missions, and other psychologically traumatic experiences arising during military service, while military sexual trauma and morally injurious experiences have also emerged as important contributors.7–9 Pharmacotherapy is a central component of coordinated PTSD care within OSI clinics, with treatment aimed at reducing symptom severity, improving quality of life, and facilitating engagement in trauma-focused psychotherapy.10,11 As the backbone of Canada’s system for treating OSIs within military populations, understanding how medications are used across these clinics is essential for ensuring consistent, high-quality care. Importantly, OSI clinics represent a unique and highly specialized treatment environment that differs from general psychiatric or community-based PTSD services. Patients treated within these clinics often present with chronic PTSD, extensive psychiatric and medical comorbidity, operational trauma exposures, and histories of multiple prior treatment attempts. As a result, prescribing practices within OSI clinics may differ from those reported in broader PTSD populations, underscoring the need for clinic-specific evidence to inform pharmacologic guidance and quality-improvement efforts in Canada.
To address these gaps, this study uses a 2-part survey of prescribing clinicians in OSI clinics across Canada to (1) evaluate prescribing patterns and their alignment with major pharmacotherapy guidelines for PTSD, including, but not limited to, the VA/DoD recommendations; and (2) examine the extent that patient characteristics, such as chronicity, comorbidities, and concurrent psychotherapy, may influence pharmacologic decisions. By examining prescribing practices within an expert network of psychiatrists (OSI clinics), this work contributes foundational evidence for future efforts to standardize treatment and refine PTSD pharmacotherapy for military and service-member populations.
METHODS
We used data from a 2-part nationwide survey of prescribing practices of psychiatrists with expertise in military PTSD and working in Canadian OSI clinics. Part 1 captured psychiatrist backgrounds and prescribing preferences, while Part 2 gathered information on patient characteristics and prescribed medications. Ethics approval for the study was obtained through the primary site, Lawson Research Institute and Western University Research Ethics Board (WREM #119200), and all participating OSI sites secured the required local approvals prior to data collection (Project #2023-2588, CIUSSS de la Capitale-Nationale; #HS25705, University of Manitoba). All findings were reviewed and codeveloped in partnership with the MIND PTSD Collaborative, a panel of clinician-researchers, psychiatrists, and psychologists with extensive experience in treating PTSD among military and RCMP populations. Reporting adhered to the Strengthening the Reporting of Observational Studies in Epidemiology guidelines.12
Participants and Recruitment
Psychiatrists were recruited through word of mouth, including email distributions within OSI networks and organizational announcements. OSI clinics across Canada were invited to participate, and psychiatrist participation was voluntary. Following removal of duplicate responses, 21 psychiatrists consented to participate and provided data for Part 1 of the study.
For Part 2, 20 of the 21 participating psychiatrists contributed clinical data on 438 patients with a primary diagnosis of PTSD receiving care at OSI clinics in Toronto/London, Winnipeg, and Quebec/Saguenay. Data were collected over an 8-week period. Each eligible patient was included once, and no repeated measures were obtained.
Eligibility Criteria
Psychiatrists were eligible to participate if they were (1) at least 18 years of age, (2) able to speak and write in English or French, and (3) currently practicing within a Canadian OSI clinic with an active caseload of patients receiving treatment for PTSD. For participation in Part 2, psychiatrists were additionally required to practice at an OSI clinic that had obtained local ethics approval for the collection of de-identified patient-level data. Individuals were excluded if eligibility criteria were not met or if consent procedures were incomplete or declined.
Pharmacologic Classes and Antidepressant Subclasses
Medication classifications were determined using information from UpToDate and Medscape, in collaboration with the MIND PTSD Collaborative. Each medication was assigned to a pharmacologic class or subclass through group consensus. In cases where medications serve multiple clinical purposes (eg, trazodone as antidepressant vs. hypnotic), classification was based on the intended indication and dosage prescribed. Pharmacologic classes included antiadrenergics, anticonvulsants, antidepressants, antipsychotics, benzodiazepines, cannabinoids, hypnotics, nonbenzodiazepine anxiolytics, psychostimulants, vasodilators, and an “other” category for medications prescribed for PTSD that did not fit within the defined groupings. Due to limited representation across most subclasses, statistical comparisons were restricted to antidepressant subclasses, which included atypical antidepressants, SNRIs, SSRIs, tricyclic antidepressants, and monoamine oxidase inhibitors.
Data Analysis
Descriptive statistics were used to summarize psychiatrist and patient characteristics, medication prescriptions, and pharmacologic classifications. Categorical variables were reported as frequencies and percentages, and continuous variables as means with standard deviations (SDs). Group differences in continuous variables were assessed using analysis of variance for comparisons involving more than 2 groups or the Kruskal-Wallis test when group sizes were <30. For 2-group comparisons, independent t-tests were used, with Fisher exact test applied when expected cell counts were <5. Differences in categorical variables were evaluated using the χ2 test. A P value <.05 was considered statistically significant. All analyses were conducted in R version 4.5.2. UpSet plots were used to summarize the most frequent intersections of concurrently prescribed medication classes.
RESULTS
Psychiatrist Characteristics
Among the 20 psychiatrists who completed the study, the majority were male (n = 13, 65%), with an average of 19.65 years (SD = 12.68) of experience as licensed psychiatrists. Participants practiced across multiple OSI clinic sites in Canada, including Quebec/Saguenay (n = 8, 40%), Toronto/London (n = 6, 30%), Winnipeg (n = 4, 20%), and Calgary (n = 2, 10%). These participating sites were included based on local research and ethics capacity and the availability of psychiatrists able to contribute de-identified prescribing data during the study period. Given the specialized and relatively small nature of the Canadian OSI clinic network, findings should be interpreted as reflective of participating sites and may not fully represent prescribing practices across all Canadian OSI clinics.
Factors Influencing Medication Prescribing for PTSD
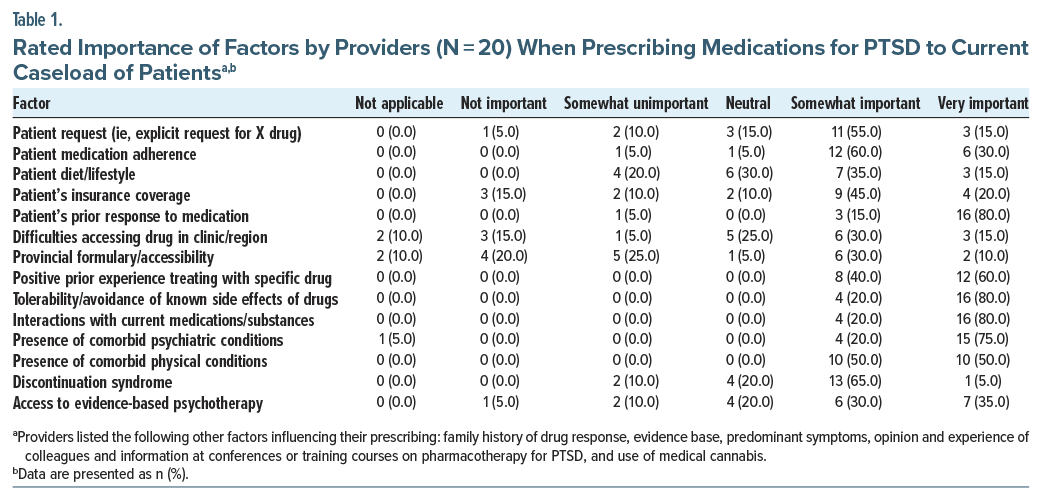
Psychiatrists were asked to rate the importance of several factors when prescribing medications for their current PTSD caseload (Table 1). Positive prior experience with a specific medication; tolerability and avoidance of known side effects; potential interactions with current medications or substances; and the presence of comorbid physical conditions were universally rated as important (“somewhat” or “very”). Factors most frequently rated as “not important” or “somewhat unimportant” included provincial formulary/accessibility (n = 9 psychiatrists, 45%); patient’s insurance coverage (n = 5, 25%); difficulties accessing the drug in their clinic or region (n = 4, 20%); and patient diet and lifestyle (n = 4, 20%). Psychiatrists also identified additional factors influencing their prescribing decisions, including family history of drug response, the available evidence base, predominant symptoms, the opinions and experiences of colleagues, information at conferences or training courses on PTSD pharmacotherapy, and the use of medicinal cannabis.
Patient Demographics, PTSD History, and Comorbidities
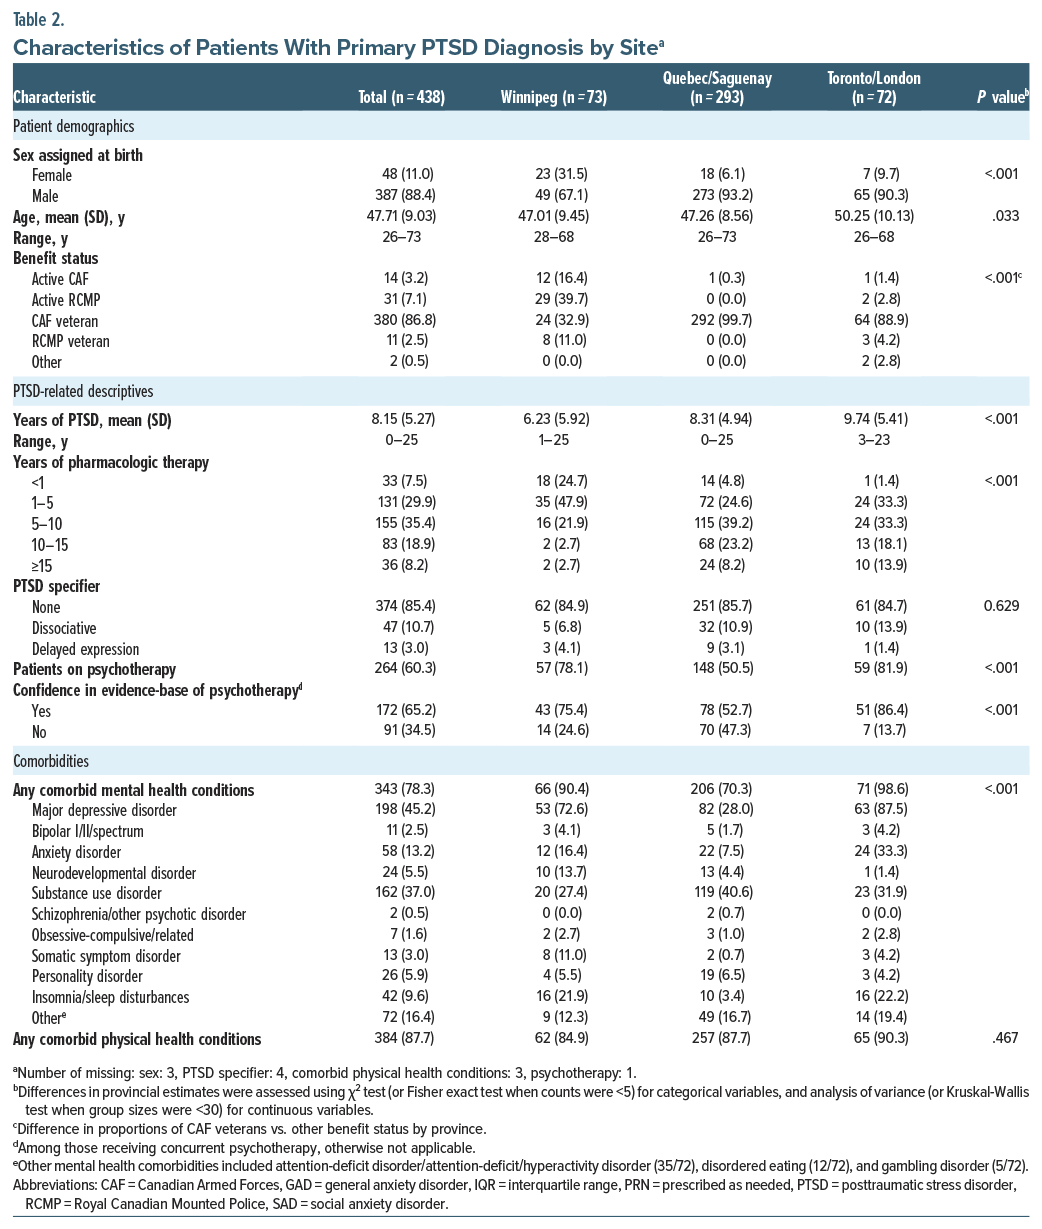
Of the patient data provided (Table 2), the majority were male (n = 387, 88.4%) and Canadian Armed Forces (CAF) veterans (n = 380, 86.8%) with a mean age of 47.71 years (SD = 9.03). The average chronicity of PTSD was 8.15 years (SD = 5.27), and over half (n = 274, 62.6%) had received pharmacologic treatment for PTSD for ≥5 years. Most patients had at least 1 comorbid mental health condition (n = 343, 78.3%).
Medication Prescriptions by Class and Type
Prescription frequencies by medication class are summarized in Table 3. The most frequently prescribed medications across all indications were bupropion (n = 92); quetiapine (n = 87); and agents commonly used for sleep, including low-dose trazodone (n = 122), zopiclone (n=123), and zolpidem (n = 84). When limited to prescriptions explicitly indicated for PTSD, the most frequently prescribed medications were doxazosin (n = 81), quetiapine (n = 78), low-dose trazodone used as a hypnotic (n = 116), zopiclone (n = 112), and zolpidem (n = 82). Of 438 patients, 432 were prescribed at least 1 medication (98.6%).
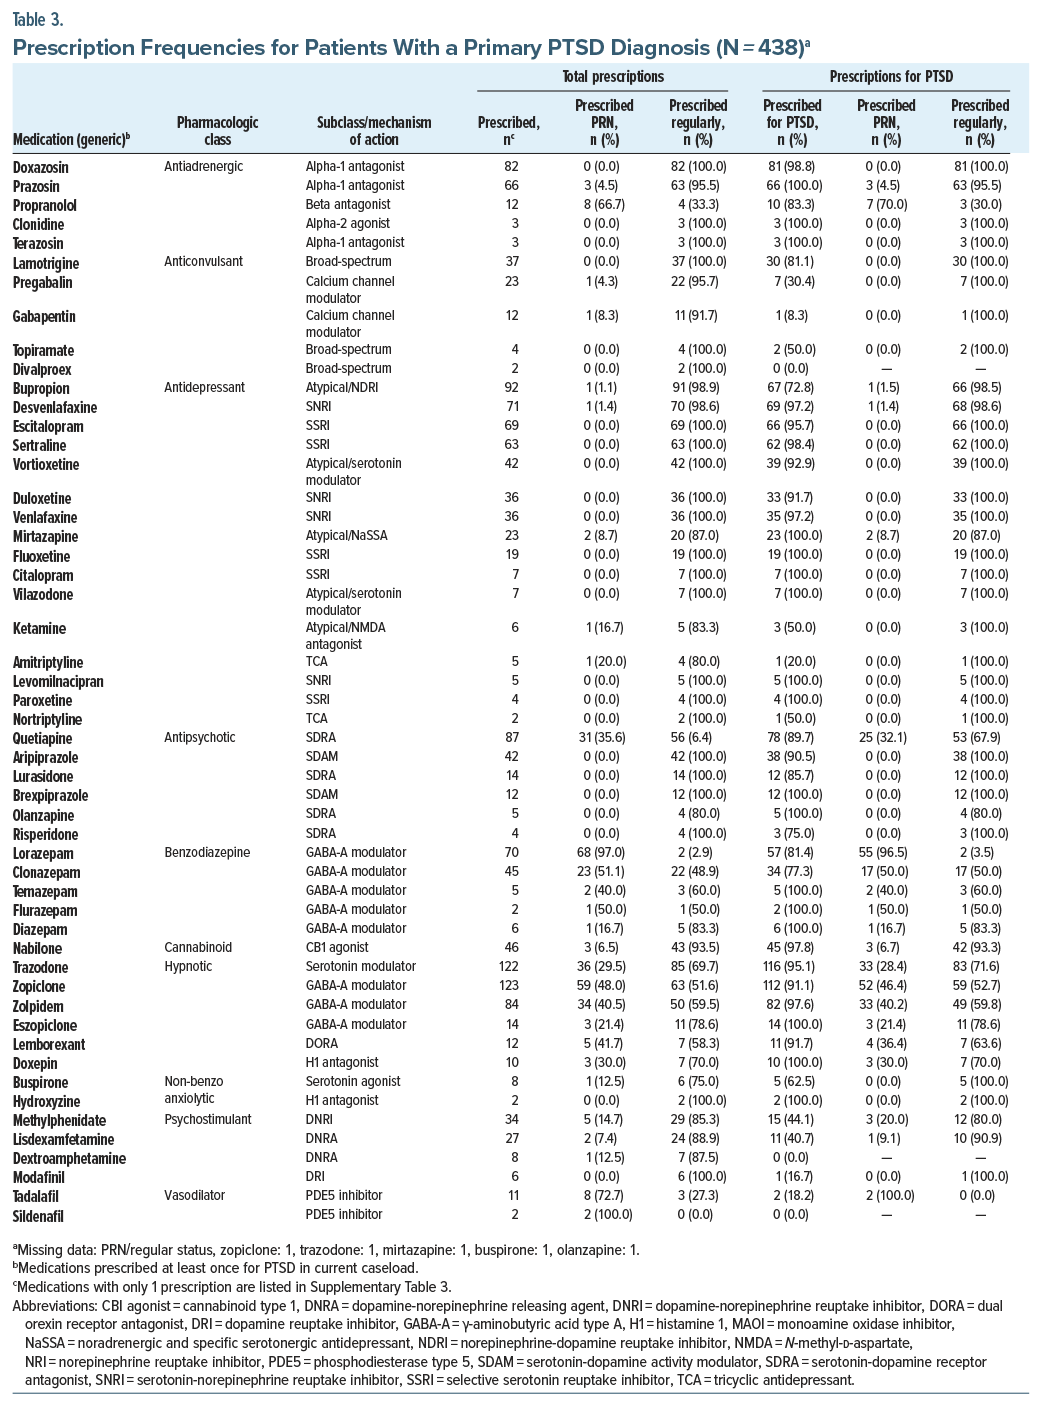
The average number of medications prescribed per patient was 3.69 (SD = 1.78) for any condition and 3.04 (SD = 1.65) specifically for PTSD. Supplementary Figure S1 displays the distribution of as-needed and routinely prescribed medications per patient by site, with corresponding counts provided in Supplementary Table S1. Antidepressants and hypnotics were the most frequently prescribed classes for both any condition and PTSD. Among patients prescribed ≥1 antidepressant (n = 394), 96.4% (n = 380) were for PTSD; for those prescribed ≥2 antidepressants (n = 89), 66.3% (n = 59) were for PTSD. Among patients prescribed ≥1 hypnotic (n = 283), 94.0% (n = 266) were for PTSD; nearly all of those prescribed ≥ 2 hypnotics (n = 77) had them prescribed for PTSD (96.1%). Few patients received multiple medications from other pharmacologic classes.
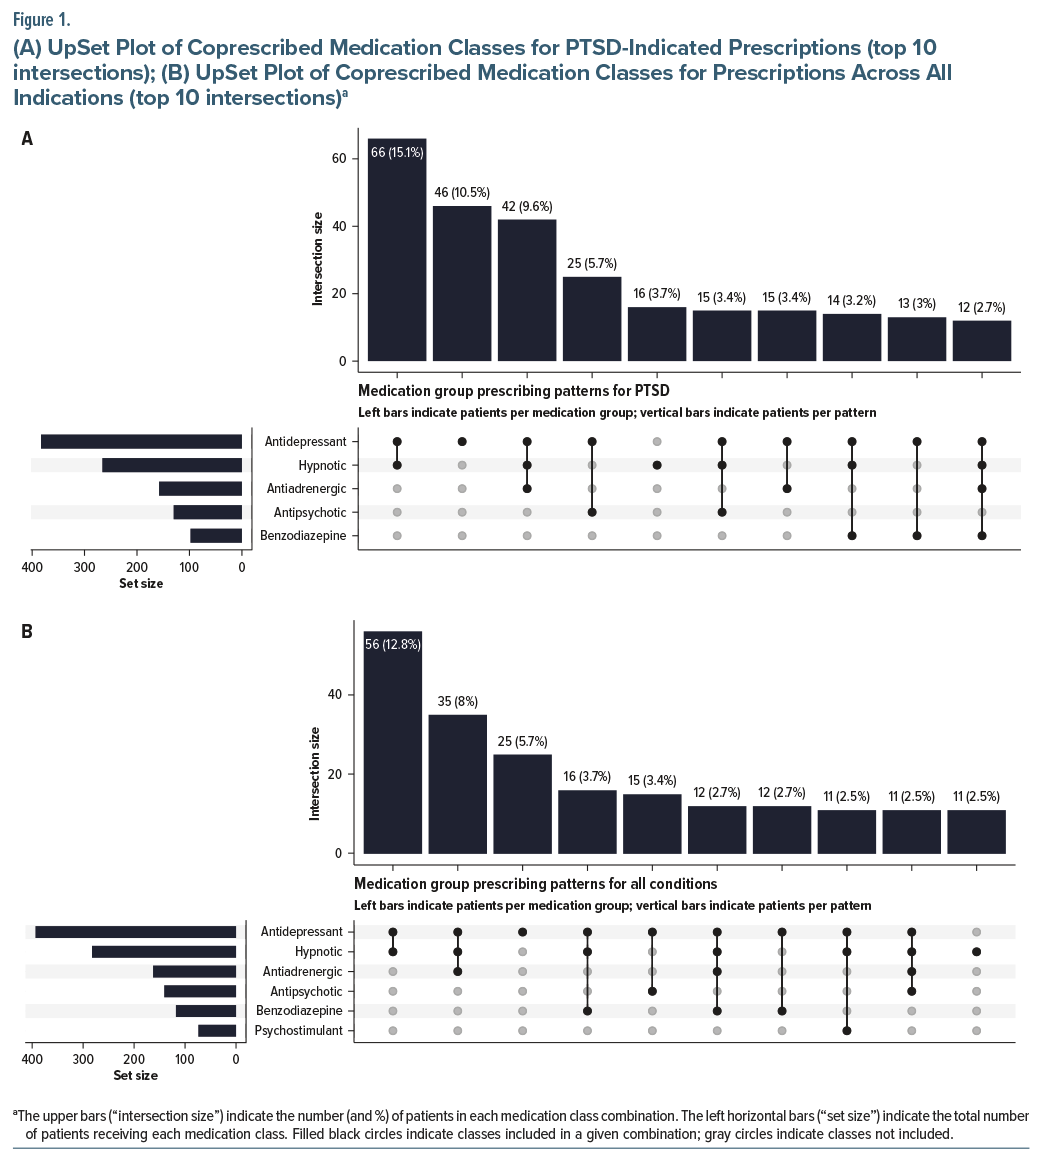
To characterize common combinations of medication classes (rather than counts by class alone), we visualized coprescribing patterns using UpSet plots, which display the most frequent class intersections among PTSD-indicated prescriptions (Figure 1A) and among prescriptions for any indication (Figure 1B). Across both figures, antidepressants and hypnotics were the most common coprescribed foundation, with additional intersections involving antiadrenergics, antipsychotics, and benzodiazepines observed among higher-complexity regimens.
Supplementary Figure S2 A–D show the top 10 medications among patients grouped by the number of PTSD-related prescriptions. Among those prescribed only 1 medication for PTSD (n = 59), the most common were sertraline (15.3%), vortioxetine (10.2%), and trazodone (10.2%). Among those prescribed 2–3 medications (n = 230), the top medications were zopiclone (25.7%), trazodone (21.7%), and zolpidem (15.7%). Among those prescribed 4–5 medications (n = 104), trazodone (42.3%), zopiclone (34.6%), and doxazosin (31.7%) were most frequent. Among patients prescribed 6–9 medications (n = 34), the most common were nabilone (52.9%), doxazosin (52.9%), and trazodone (47.1%). Coprescribed medication classes among patients on SSRIs (n = 158) and SNRIs (n = 142) are shown in Supplementary Figures S3A and S3B. The 5 most frequently coprescribed classes were as follows: hypnotics (SSRIs: 63.9%, SNRIs: 66.2%), antiadrenergics (SSRIs: 41.1%, SNRIs: 40.1%), antipsychotics (SSRIs: 27.2%, SNRIs: 28.2%), benzodiazepines (SSRIs: 19.6%, SNRIs: 24.6%), and atypical antidepressants (SSRIs: 13.9%, SNRIs: 19.7%).
Comparison of Medication Prescriptions By Site
Supplementary Table S2 presents the number and proportion of unique patients prescribed each medication by site. Statistical comparisons were conducted for each pharmacologic class and antidepressant subclass. Significant differences (P < .001) by site were observed across most classes and subclasses, indicating substantial variability in prescribing patterns.
DISCUSSION
This study provides a national, multisite examination of prescribing practices for PTSD among CAF and RCMP patients treated within OSI clinics across Canada. Across engaged sites, antidepressants were the most commonly prescribed medication class for PTSD, with SSRIs and SNRIs frequently used, particularly among patients prescribed fewer medications. These patterns are consistent with current guideline recommendations that identify SSRIs and SNRIs as preferred first-line therapies. However, the results also demonstrate considerable variability in prescribing practices, including high rates of polypharmacy, substantial variability in medication selection, frequent use of medication outside guideline-supported recommendations, and significant variation in prescribing based on patient characteristics, such as chronicity, comorbidities, and prior treatment history. These findings show that while evidence-informed guidelines may form the foundation of care, actual prescribing decisions reflect the complexities commonly seen in military-related PTSD. Importantly, this study extends existing PTSD prescribing literature by providing the first national, multisite examination of pharmacotherapy practices across Canada’s specialized OSI clinic network, offering insight into how clinicians adapt guideline-based recommendations within highly complex military and veteran populations. However, these findings should be interpreted within the context of participating OSI clinics and may not fully generalize to all psychiatrists practicing across the broader Canadian OSI clinic network.
Current Patterns of Medication Selection and Use
Patients in this sample had an average PTSD duration of over 8 years, high comorbidity rates, and extensive treatment histories, with nearly two-thirds receiving pharmacotherapy for 5 or more years. In this context, the finding that many patients were prescribed 3 or more PTSD-related medications likely reflects efforts to address persistent and complex symptom clusters, such as sleep disturbance, nightmares, hyperarousal, and mood dysregulation, rather than reliance on monotherapy to address overall PTSD symptoms. This aligns with international literature showing that single-agent pharmacotherapy is often insufficient for military-related PTSD and that multimodal medication combinations are frequently required in routine practice.13,14
Convergence With and Divergence From Guideline Recommendations
Consistent with international guidelines, SSRIs and SNRIs were widely prescribed and often formed the basis of treatment regimens, particularly among patients receiving fewer medications. These findings are broadly aligned with prescribing patterns reported in other military and veteran PTSD treatment settings internationally,15–17 including within the US Veterans Health Administration, where antidepressants remain the cornerstone of pharmacologic management.
At the same time, prescribing patterns diverged from guideline recommendations in several ways that appear consistent with symptom-targeted prescribing. Hypnotics, antipsychotics, and benzodiazepines were prescribed at notable rates despite limited guideline support. Hypnotics were commonly prescribed for PTSD itself, particularly in Quebec/Saguenay, which may reflect clinicians’ attempts to address the persistent and debilitating sleep disturbances associated with chronic PTSD. Benzodiazepines, although discouraged across guidelines due to risks and limited evidence of efficacy, were prescribed selectively, often in as-needed form, suggesting potential use in response to acute anxiety, panic, or crisis presentations.
Taken together, these divergences appear to reflect clinical complexity and patient needs rather than indiscriminate deviation from evidence. Patients with chronic, refractory PTSD often cycle through multiple first-line options; adjunctive agents may be introduced when guideline-supported therapies prove insufficient, poorly tolerated, or slow to act. Similar patterns of adjunctive prescribing and polypharmacy have been reported in other military-related PTSD populations15,17,18 and likely reflect the substantial chronicity, comorbidity, and symptom burden encountered in specialized operational trauma settings.
Collectively, these findings suggest that while SSRIs and SNRIs remain central to PTSD treatment within OSI clinics, prescribing practices often extend beyond first-line recommendations. For many patients, standard treatments (eg, SSRIs, SNRIs, and trauma-focused psychotherapies) do not fully relieve persistent symptoms, leading psychiatrists to incorporate adjunctive medications to target severe insomnia, nightmares, hyperarousal, acute anxiety, and comorbid conditions. The reliance on multiple medication classes underscores the challenge of strictly adhering to guideline-based care in real-world settings, where individualized, symptom-driven treatment plans are often necessary to optimize functioning and support engagement in therapy.
Other Factors Influencing Prescribing Decisions
In our study, patient-level complexity played a major role in shaping prescribing decisions across OSI clinics. Most patients had long-standing PTSD, with an average duration exceeding 8 years, high rates of mental and physical health comorbidities, and extensive treatment histories. This chronicity of PTSD meant that many individuals continued to experience persistent symptoms despite prior trials of first-line treatments. The high prevalence of comorbid conditions, particularly major depressive disorder, anxiety disorders, chronic pain, and substance use, also required clinicians to tailor regimens to overlapping symptom domains. In this context, adjunctive medications were often used to enhance functioning or support engagement in psychotherapy when first-line SSRIs or SNRIs alone were insufficient. Long treatment histories further contributed to this pattern, as many patients had previously cycled through multiple first-line agents, experienced partial responses, or required maintenance therapy to prevent relapse.
In addition to individual complexities, site-level differences were observed in both the types and frequencies of medications prescribed. Sites varied substantially in the proportion of active CAF members, RCMP members, and veterans, each of whom may present with different clinical needs, operational constraints, and tolerability concerns. For example, active-duty personnel often require medications with minimal cognitive or sedative side effects to maintain operational readiness, whereas veterans with long-standing, treatment-resistant PTSD may prioritize symptom relief over functional restrictions. These population differences likely contributed to the differences in patient characteristics and prescribing practices observed in Winnipeg compared with Quebec/Saguenay. Within the Canadian OSI network, clinics may serve different patient populations depending on region and referral pathways, including active-duty CAF members, veterans, and RCMP personnel, which may influence clinical presentation and prescribing considerations across sites.
Limitations and Strengths
This study represents the first national, multisite examination of prescribing practices for PTSD care in OSI clinics. While its collaborative codesign, multiclinic participation across different provinces, and a large patient sample were inherent strengths, a number of limitations were still evident and should be weighed against the current findings.
First, the cross-sectional design limits the ability to draw causal inferences regarding the relationships between patient characteristics, provider decision-making, and prescribing decisions. Second, although detailed prescribing data were obtained, the study was unable to capture the full scope of psychiatrists’ clinical reasoning, particularly in cases where treatment deviated from guideline recommendations. As data were derived from electronic medical records, nuances in decision-making and provider rationales were not systematically documented. Third, the study did not examine the role of psychotherapy, which may have significantly influenced pharmacologic strategies. Fourth, variability in prescribing across OSI clinics may partly reflect underlying differences in patient demographics, which were not fully explored. Additionally, though psychiatrists were recruited from participating OSI clinics across several Canadian provinces, findings may not fully represent prescribing practices across the broader Canadian OSI clinic network. For instance, participation in both parts of the survey required psychiatrists to practice at clinics with local ethics approval for the collection of de-identified patient-level data, which may have disproportionately favored larger urban centers with greater research infrastructure and administrative capacity, thereby limiting generalizability to smaller or rural clinics. Further, information regarding psychiatrists’ employment status (eg, full-time vs. part-time practice) was not collected, limiting the ability to assess whether differences in practice arrangements contributed to prescribing variability or affected the generalizability of findings. Finally, contextual factors such as access to trauma-focused psychotherapies, institutional resource constraints, and variability in medication coverage were not systematically assessed, yet may have contributed to the observed differences in prescribing practices.
Conclusions and Implications for Clinical Care and Practice
This study highlights the tension between balancing guideline adherence and the need to tailor treatment to the complexities of individual patients in routine clinical practice. While SSRIs and SNRIs remain central to PTSD treatment in OSI clinics, psychiatrists appear to tailor prescribing strategies to address chronic symptoms, comorbid conditions, and prior treatment experiences. These findings suggest that more flexible clinical guidance may better reflect the realities of treating military populations with complex PTSD.
Given the high levels of comorbidity within military and veteran populations, efforts to standardize care may benefit from moving beyond a strict first-line and second-line paradigm toward a stepped or phased model that better reflects the complexity and chronicity seen in real-world settings. Such an approach could provide clearer guidance on when adjunctive agents are justified, how medications may be sequenced or combined, and how polypharmacy can be managed safely over time. However, developing this kind of guidance will require a stronger empirical foundation, including pragmatic trials examining sequenced and combined pharmacologic strategies.
The marked site-level variation in prescribing further underscores the need for targeted quality-improvement efforts across the OSI network. Implementation research suggests that prescribing guideline uptake is shaped by multiple behavioral determinants, including environmental constraints, guideline complexity, knowledge and awareness, social influences, and clinician disagreement, which can contribute to variation in real-world prescribing.6,19 Tailored strategies such as audit-and- feedback, shared case review, and cross-clinic consensus-building may therefore help improve consistency in care. At the same time, it will be important to distinguish variation that reflects legitimate patient need from variation driven by local practice culture or system constraints.
Because Canada currently lacks a unified, Canadian-specific pharmacotherapy guideline for military-related PTSD, these findings provide an important foundation for developing guidance that integrates international evidence with real-world OSI prescribing patterns. Such guidance should explicitly situate pharmacotherapy within a broader model of multidisciplinary care, linking medication strategies with trauma-focused psychotherapies, sleep interventions, and other nonpharmacologic supports to better meet the needs of CAF and RCMP members and veterans.
Article Information
Published Online: November 5, 2026. https://doi.org/10.4088/PCC.26m04242
© 2026 Physicians Postgraduate Press, Inc.
Submitted: March 3, 2026; accepted June 22, 2026.
To Cite: Liu JJW, Collins E, Ein N, et al. Prescription patterns in Canadian operational stress injury clinics: an in-depth examination of posttraumatic stress disorder treatment practices.
Prim Care Companion CNS Disord 2026;28(6):26m04242.
Author Affiliations: MacDonald Franklin OSI Research Centre, Lawson Research Institute, London, Ontario, Canada (Liu, Collins, Ein, Gargala, Nazarov, Le, Easterbrook, Richardson); Department of Psychiatry, Western University, London, Ontario, Canada (Liu, Collins, Ein, Nazarov, Balderson, Richardson); Department of Psychiatry and Behavioural Neurosciences, McMaster University, Hamilton, Ontario, Canada (Nazarov, Richardson); Department of Psychology, Neuroscience and Behaviour, McMaster University, Hamilton, Ontario, Canada; Clinique TSO du CIUSSS de la Capitale Nationale, Québec, Canada (Auger, Bilodeau, Lavoie); Département de Psychiatrie et de Neurosciences, Faculté de Médecine, Université Laval, Québec, Canada (Auger, Bilodeau); St. Joseph’s OSI Clinic, St. Joseph’s Health Care London, London, Ontario, Canada (Balderson, Wanklyn, Richardson); Department of Psychiatry, University of Toronto, Toronto, Ontario, Canada (Burhan); Ontario Shores Centre of Mental Health Sciences, Whitby, Ontario (Burhan); Department of Psychiatry, Max Rady College of Medicine, University of Manitoba, Winnipeg, Manitoba, Canada (Enns); Deer Lodge Centre OSI Clinic, Winnipeg, Manitoba, Canada (Enns, Mota); Department of Clinical Health Psychology and Psychiatry, University of Manitoba, Winnipeg, Manitoba, Canada (Mota); Lawson Research Institute, London, Ontario, Canada (Wanklyn).
Corresponding Author: Jenny J. W. Liu, PhD, The Macdonald Franklin OSI Research Centre, Finch Mental Health Care Building, Parkwood Institute, St. Joseph’s Health Care London, 55 Wellington Rd, F4-367, London, ON N6C 0A7 ([email protected]).
Financial Disclosure: None.
Funding/Support: This work was supported by the Atlas Institute for Veterans and Families (Ottawa, Ontario, Canada) and the St. Joseph’s Health Care Foundation (London, Ontario, Canada).
Role of the Sponsor: The sponsors had no role in the design, conduct, analysis, interpretation, or publication of this study.
Previous Presentations: A portion of the evidence was presented at the CIMVHR Forum (Ottawa, Ontario, Canada; October 2025) and the Canadian Psychiatric Association Annual Conventions (Vancouver, British Columbia, Canada; October 2025).
Supplementary Material: Available at Psychiatrist.com.
Clinical Points
- Pharmacotherapy for posttraumatic stress disorder (PTSD) within Canadian operational stress injury (OSI) clinics commonly involves polypharmacy and adjunctive medication use, particularly among patients with chronic PTSD, extensive treatment histories, and psychiatric comorbidities.
- Although selective serotonin reuptake inhibitors and serotonin-norepinephrine reuptake inhibitors remain the foundation of PTSD treatment, clinicians frequently incorporate symptom-targeted agents (eg, hypnotics, antiadrenergics, and antipsychotics) to address persistent insomnia, nightmares, hyperarousal, and comorbid symptoms.
- Substantial variation in prescribing across OSI clinics highlights the need for clearer pragmatic guidance, shared case review, and cross-site quality-improvement strategies to support consistent, evidence-informed care while preserving individualized clinical judgment.
Journal of Clinical Psychiatry, all rights reserved.